
Zoladex 10.8 mg Implant
Brand Information
| Brand name | Zoladex 10.8 mg Implant |
| Active ingredient | Goserelin, Goserelin |
| Schedule | S4 |
Consumer Medicine Information (CMI) leaflet
Please read this leaflet carefully before you start using the Zoladex 10.8 mg Implant.
Summary CMI
ZOLADEX® 10.8 mg Implant SafeSystem®
Consumer Medicine Information (CMI) summary
The full CMI on the next page has more details. If you are worried about using this medicine, speak to your doctor or pharmacist.
1. Why am I using ZOLADEX 10.8 mg?
ZOLADEX 10.8 mg contains the active ingredient goserelin acetate. ZOLADEX 10.8 mg is used to lower the amount of sex hormones in the body. ZOLADEX 10.8 mg is used to treat prostate cancer in some men.
For more information, see Section 1. Why am I using ZOLADEX 10.8 mg? in the full CMI.
2. What should I know before I use ZOLADEX 10.8 mg?
Do not use if you have ever had an allergic reaction to goserelin acetate or any of the ingredients listed at the end of the CMI.
Talk to your doctor if you have any other medical conditions or take any other medicines.
For more information, see Section 2. What should I know before I use ZOLADEX 10.8 mg? in the full CMI.
3. What if I am taking other medicines?
Some medicines may interfere with ZOLADEX 10.8 mg and affect how it works.
A list of these medicines is in Section 3. What if I am taking other medicines? in the full CMI.
4. How is ZOLADEX 10.8 mg given?
A ZOLADEX 10.8 mg implant will be injected into the skin of your stomach every 3 months.
More instructions can be found in Section 4. How is ZOLADEX 10.8 mg given? in the full CMI.
5. What should I know while using ZOLADEX 10.8 mg?
| Things you should do |
|
| Things you should not do |
|
| Driving or using machines |
|
| Looking after your medicine |
|
For more information, see Section 5. What should I know while using ZOLADEX 10.8 mg? in the full CMI.
6. Are there any side effects?
All medicines can have side effects. Sometimes they are serious, most of the time they are not. Tell your doctor immediately if you have trouble passing urine, feel weak in the arms or legs, feel numb in the arms or legs, have pain in the kidneys, have pain in the bones or backbone or have a tumour in your pituitary gland which causes severe headaches, sickness, loss of eyesight and unconsciousness. For more information, including what to do if you have any side effects, see Section 6. Are there any side effects? in the full CMI.
Full CMI
ZOLADEX® 10.8 mg Implant SafeSystem®
Active ingredient: goserelin acetate
Consumer Medicine Information (CMI)
This leaflet provides important information about using ZOLADEX 10.8 mg. You should also speak to your doctor or pharmacist if you would like further information or if you have any concerns or questions about using ZOLADEX 10.8 mg.
Where to find information in this leaflet:
1. Why am I using ZOLADEX 10.8 mg?
2. What should I know before I use ZOLADEX 10.8 mg?
3. What if I am taking other medicines?
4. How is ZOLADEX 10.8 mg given?
5. What should I know while using ZOLADEX 10.8 mg?
6. Are there any side effects?
7. Product details
1. Why am I using ZOLADEX 10.8 mg?
ZOLADEX 10.8 mg contains the active ingredient goserelin acetate. ZOLADEX 10.8 mg is a member of the anti-hormonal group of medicines. This means that it affects the levels of various hormones (natural chemicals produced by the body). In men it reduces the level of testosterone.
ZOLADEX 10.8 mg is used to treat prostate cancer in some men. It is not a cure for prostate cancer.
2. What should I know before I use ZOLADEX 10.8 mg?
Warnings
Do not use ZOLADEX 10.8 mg if:
- you are allergic to goserelin acetate, or any of the ingredients listed at the end of this leaflet. Always check the ingredients to make sure you can use this medicine.
Symptoms of an allergic reaction may include:
- rash
- hay fever
- difficulty breathing
- feeling faint
Check with your doctor if you:
- have any other medical conditions (have heart or blood vessel conditions, including heart rhythm problems (arrhythmia), or are being treated with medicines for these conditions). The risk of you having further heart rhythm problems may increase if you are taking ZOLADEX 10.8 mg.
- have any condition which affects the strength of your bones.
- you have had any problems passing urine or if you have had any lower back problems.
- you have diabetes.
- take any medicines for any other conditions
During treatment, you may be at risk of developing certain side effects. It is important you understand these risks and how to monitor for them. See additional information under Section 6. Are there any side effects?
Pregnancy and breastfeeding
ZOLADEX 10.8 mg will not normally be used in females. There is not enough evidence to support its use in women.
It is also unlikely that you can father a child while using ZOLADEX 10.8 mg, but you must use your normal contraceptive method to make sure.
Children
Do not give ZOLADEX 10.8 mg to children.
There is no information on its use in children.
3. What if I am taking other medicines?
Tell your doctor or pharmacist if you are taking any other medicines, including any medicines, vitamins or supplements that you buy without a prescription from your pharmacy, supermarket or health food shop.
ZOLADEX 10.8 mg might interfere with some medicines used to treat heart rhythm problems or might increase the risk of heart rhythm problems when used with some other drugs that can cause heart rhythm abnormalities.
Check with your doctor or pharmacist if you are not sure about what medicines, vitamins or supplements you are taking and if these affect ZOLADEX 10.8 mg.
4. How is ZOLADEX 10.8 mg given?
How much you will be given
- A ZOLADEX 10.8 mg implant will be injected into the skin of your stomach every 3 months.
- The implant is a very small pellet that is given by a special needle and syringe known as SafeSystem. The injection will not hurt very much.
- The pellet is designed to slowly release the medicine into your body over 3 months.
- The ZOLADEX 10.8 mg SafeSystem incorporates a protective needle sleeve that automatically locks in place following administration of the implant to help prevent needle stick injury.
If you forget to be given ZOLADEX 10.8 mg
Your doctor will make an appointment for your next dose, so you will not forget your next dose.
If you use too much ZOLADEX 10.8 mg
The doctor or nurse giving you ZOLADEX 10.8 mg will be experienced in the use of it, so it is unlikely that you will be given an overdose.
5. What should I know while using ZOLADEX 10.8 mg?
Things you should do
Make sure to keep your appointment for being given ZOLADEX 10.8 mg every 3 months.
If you do not, your testosterone level will rise and the prostate cancer may grow more quickly.
Remind any doctor, dentist or pharmacist you visit that you are using ZOLADEX 10.8 mg.
Things you should not do
- Do not stop being given ZOLADEX 10.8 mg unless you have discussed it with your doctor first.
They will have explained why you need to be given ZOLADEX 10.8 mg and for how long. - Do not use if the packaging is torn or shows signs of tampering.
Driving or using machines
Be careful before you drive or use any machines or tools until you know how ZOLADEX 10.8 mg affects you.
Looking after your medicine
- Keep in a cool, dry place where the temperature stays below 25°C.
Follow the instructions in the carton on how to take care of your medicine properly.
Store it in a cool dry place away from moisture, heat or sunlight; for example, do not store it:
- in the bathroom or near a sink, or
- in the car or on window sills.
Keep it where young children cannot reach it.
Getting rid of any unwanted medicine
If you no longer need to use this medicine or it is out of date, take it to any pharmacy for safe disposal.
Do not use this medicine after the expiry date.
6. Are there any side effects?
All medicines can have side effects. If you do experience any side effects, most of them are minor and temporary. However, some side effects may need medical attention.
See the information below and, if you need to, ask your doctor or pharmacist if you have any further questions about side effects.
Serious side effects
| Serious side effects | What to do |
Tell your doctor immediately if any of these things happen while you are using ZOLADEX 10.8 mg:
These may mean that the cancer is growing.
| Call your doctor straight away, or go straight to the Emergency Department at your nearest hospital if you notice any of these serious side effects. |
You may experience the following side effects:
| Less serious side effects | What to do |
| Speak to your doctor if you have any of these very common side effects and they worry you. |
ZOLADEX 10.8 mg lowers the amount of sex hormones in your body so your sex drive will probably be reduced.
Tell your doctor or pharmacist if you notice anything else that may be making you feel unwell.
Other side effects not listed here may occur in some people.
Reporting side effects
After you have received medical advice for any side effects you experience, you can report side effects to the Therapeutic Goods Administration online at www.tga.gov.au/reporting-problems. By reporting side effects, you can help provide more information on the safety of this medicine.
Always make sure you speak to your doctor or pharmacist before you decide to stop taking any of your medicines.
7. Product details
This medicine is only available with a doctor's prescription.
What ZOLADEX 10.8 mg contains
| Active ingredient (main ingredient) | goserelin (as the acetate) |
| Other ingredients (inactive ingredients) | polyglactin |
Do not take this medicine if you are allergic to any of these ingredients.
What ZOLADEX 10.8 mg looks like
ZOLADEX 10.8 mg (AUST R 55242) comes in a special syringe, called the SafeSystem, and a siliconised needle.
The small pellet containing ZOLADEX 10.8 mg is about the size of a grain of rice. It can be seen in the "window" half way up the syringe and is white or cream coloured.
Who distributes ZOLADEX 10.8 mg
AstraZeneca Pty Ltd
ABN 54 009 682 311
66 Talavera Road
MACQUARIE PARK NSW 2113
Telephone:- 1800 805 342
This leaflet was prepared in March 2026.
Zoladex, Zoladex SafeSystem and SafeSystem are trade marks of the AstraZeneca group of companies.
© AstraZeneca 2026
VV-RIM-06055551 v 4.0
Brand Information
| Brand name | Zoladex 10.8 mg Implant |
| Active ingredient | Goserelin, Goserelin |
| Schedule | S4 |
MIMS Revision Date: 01 October 2026
1 Name of Medicine
Goserelin acetate.
2 Qualitative and Quantitative Composition
Each Zoladex SafeSystem Implant contains goserelin 10.8 mg (as goserelin acetate).
For the full list of excipients, see Section 6.1 List of Excipients.
3 Pharmaceutical Form
A sterile white to cream coloured cylindrical sustained release implant in which goserelin acetate is dispersed in a polyglactin co-polymer biodegradable matrix.
The implant is supplied in a single dose syringe applicator. The SafeSystem incorporates a protective needle sleeve that automatically locks in place following administration of the implant to aid in the prevention of needle stick injury.
4 Clinical Particulars
4.1 Therapeutic Indications
Prostate cancer. Palliative treatment of metastatic (M+) or locally advanced prostate cancer where suitable for hormonal manipulation.
Adjuvant and neoadjuvant therapy in combination with radiotherapy for the management of locally advanced prostate cancer in men suitable for hormonal manipulation.
Breast cancer. Management of oestrogen-receptor (ER) positive early and advanced breast cancer in pre and peri menopausal women.
4.2 Dose and Method of Administration
Caution should be taken while inserting Zoladex into the anterior abdominal wall due to the proximity of underlying inferior epigastric artery and its branches. Do not penetrate into muscle or peritoneum.
The Zoladex syringe cannot be used for aspiration. If the hypodermic needle penetrates a large vessel, blood will be seen instantly in the syringe chamber. If a vessel is penetrated, withdraw the needle and immediately control any resultant bleeding, monitoring the patient for signs or symptoms of abdominal haemorrhage. After ensuring the patient is haemodynamically stable, another Zoladex implant may be injected with a new syringe elsewhere.
Use extra care when administering Zoladex to patients with a low BMI and/or who are receiving full anticoagulation medication (see Section 4.4 Special Warnings and Precautions for Use).
Before injection, it should be ensured that the implant is visible in the window of the applicator. The plunger should not be withdrawn once the needle is in position. The plunger should be fully depressed to expel the implant into subcutaneous tissue, well away from point of entry and to activate the protective needle sleeve.
For correct administration of Zoladex, see instructions on the administration card.
Do not omit or delay injections, as serum testosterone or serum oestradiol levels may rise in males and females respectively.
In the unlikely event of the need to surgically remove a Zoladex implant, it may be localised by ultrasound.
Prostate cancer. One implant of Zoladex 10.8 mg injected subcutaneously into the anterior abdominal wall, every 3 months (see Section 5.1 Pharmacodynamic Properties). Adjuvant and/or neoadjuvant Zoladex therapy in combination with radiotherapy may include short-term use of an anti-androgen to prevent flare (see Section 5.1 Pharmacodynamic Properties, Clinical trials, Prostate cancer - adjuvant and neoadjuvant Zoladex therapy in combination with radiotherapy).
Breast cancer. One implant of Zoladex 10.8 mg injected subcutaneously into the anterior abdominal wall, every 12 weeks.
Special patient populations. Renal impairment. No dosage adjustment is necessary for patients with renal impairment.
Hepatic impairment. No dosage adjustment is necessary for patients with hepatic impairment.
Use in the elderly. No dosage adjustment is necessary in the elderly.
Paediatric use. Zoladex 10.8 mg Implant is not indicated for use in children.
4.3 Contraindications
Zoladex is contraindicated in patients with known hypersensitivity to luteinising hormone releasing hormone (LHRH), LHRH agonist analogues or any of the components of Zoladex.
Pregnancy and lactation (see Section 4.6 Fertility, Pregnancy and Lactation).
4.4 Special Warnings and Precautions for Use
Injection site injury has been reported with Zoladex, including events of pain, haematoma, haemorrhage and vascular injury. Monitor affected patients for signs or symptoms of abdominal haemorrhage. In very rare cases, administration error resulted in vascular injury and haemorrhagic shock requiring blood transfusions and surgical intervention.
Extra care should be taken when administering Zoladex to patients with a low BMI and/or receiving full anticoagulation medications (see Section 4.2 Dose and Method of Administration).
Serum testosterone concentrations in males or serum oestradiol concentrations in females may rise if an implant is omitted or delayed.
Advanced or metastatic breast or prostate cancer. Initially, Zoladex, like other LHRH agonists, transiently increases serum testosterone in males and serum oestradiol in females. Although not necessarily associated, there have been reports of temporary increase in bone pain in patients with advanced cancer and bony metastases. These events may last up to two weeks and may need to be managed symptomatically. Some patients may experience a temporary increase in tumour signs and symptoms, which can be managed symptomatically. Rarely, patients with bony metastases have developed hypercalcaemia on initiation of therapy.
For prostate cancer, the use of Zoladex in patients with metastatic cancer who are at particular risk of developing ureteric obstruction or spinal cord compression should be considered carefully and the patients monitored closely during the first month of therapy. If spinal cord compression or renal impairment due to ureteric obstruction are present or develop, specific standard treatment of these complications should be instituted. Isolated cases of short-term worsening of these signs and symptoms have been reported during the initial four weeks of Zoladex therapy. Consideration should be given to anti-androgen therapy at the start of Zoladex therapy since this has been reported to prevent the possible sequelae of the initial rise in serum testosterone.
Hyperglycaemia and diabetes. Hyperglycaemia and an increased risk of developing diabetes have been reported in men receiving gonadotrophin releasing hormone (GnRH) agonists. Hyperglycaemia may represent development of diabetes mellitus or worsening of glycaemic control in patients with diabetes. Monitor blood glucose and/or glycosylated haemoglobin (HbA1c) periodically in patients receiving a GnRH agonist and manage with current practice for the treatment of hyperglycaemia or diabetes.
Cardiovascular disease. An increased risk of developing myocardial infarction, sudden cardiac death and stroke has been reported in association with use of GnRH agonists in men. The risk appears low based on the reported odds ratios and should be evaluated carefully along with cardiovascular risk factors when determining a treatment for patients with prostate cancer. Patients receiving a GnRH agonist should be monitored for symptoms and signs suggestive of development of cardiovascular disease and managed according to current clinical practice.
Bone mineral density. The use of Zoladex causes loss of bone mineral density (BMD). Currently available data suggest that recovery of bone loss occurs after cessation of therapy.
Following two years treatment with Zoladex (3.6 mg every 28 days) for early breast cancer, the average loss of bone mineral density was 6.2% and 11.5% at the femoral neck and lumbar spine respectively. This loss has been shown to be partially reversible at the one year off treatment follow-up with recovery to 3.4% and 6.4% below baseline at the femoral neck and lumbar spine respectively.
Particular care should be taken in assessing patients for treatment if they exhibit risk factors for osteoporosis such as family history, slight build, heavy smoking and low dietary calcium intake or in women with chronic anovulatory menstrual disturbances, patients treated with glucocorticoids, or chronically immobilised. Patients with significant risk factors should have bone density measured before commencing treatment. The clinician should discuss relevant risk factors with patients on an individual basis.
QT/QTc interval prolongation. Androgen deprivation therapy may prolong QT/QTc interval. Prescribers should consider whether the benefits of androgen deprivation therapy outweigh the potential risks in patients with congenital long QT syndrome, congestive heart failure, frequent electrolyte abnormalities and in patients taking drugs known to prolong the QT interval. Electrolyte imbalances should be corrected. Consider periodic monitoring of electrocardiograms and electrolytes (see Section 4.5 Interactions with Other Medicines and Other Forms of Interactions).
Vaginal bleeding. During early treatment with goserelin acetate some women may experience vaginal bleeding of variable duration and intensity. Such bleeding probably represents oestrogen withdrawal bleeding and is expected to stop spontaneously. If bleeding continues, the reason should be investigated.
During treatment with LHRH analogues patients may enter the natural menopause. Rarely, menstruation does not resume on cessation of Zoladex therapy.
Use in the elderly. See Section 4.2 Dose and Method of Administration.
Paediatric use. Zoladex is not indicated for use in children as safety and efficacy have not been established in this group of patients.
Effects on laboratory tests. No data available.
4.5 Interactions with Other Medicines and Other Forms of Interactions
No data available.
Since androgen deprivation treatment may prolong the QT interval, the concomitant use of Zoladex with medicinal products known to prolong the QT interval or medicinal products able to induce Torsades de Pointes should be carefully evaluated (see Section 4.4 Special Warnings and Precautions for Use).
4.6 Fertility, Pregnancy and Lactation
Effects on fertility. The expected pharmacology of Zoladex is the suppression of gonad function to castrate levels. As a result there is profound impairment of fertility.
In rats this is expressed as:
Male. Decrease in weight and atrophic histological changes in the testes, epididymis, seminal vesicle and prostate gland with complete suppression of spermatogenesis.
Female. Suppression of ovarian function with decreased size and weight of the ovaries and secondary sex organs; arrest of follicular development at the antral stage and reduction in size and number of the corpora lutea.
Except for the testes, almost complete reversal of these effects in male and female rats was observed several weeks after dosing was stopped, however, fertility and general reproductive performance were reduced in those that became pregnant after goserelin was discontinued.
Based on histological examination, drug effects on reproductive organs seem to be completely reversible in male and female dogs when drug treatment was stopped after continuous administration for 1 year at doses equivalent to 214 microgram/kg/day (approximately 24 times the recommended human dose based on AUC).
Use in pregnancy. (Category D)
(See Section 4.3 Contraindications.)
Zoladex should not be used in pregnancy as there is a theoretical risk of pregnancy loss or fetal abnormality if LHRH agonists are used during pregnancy. A pregnancy test should be performed prior to administering the Zoladex implant in patients who could become pregnant.
Patients who could become pregnant should use non-hormonal contraceptive methods during treatment with Zoladex and until resumption of menstruation following discontinuation of treatment with Zoladex. Time to return of menses after cessation of therapy with Zoladex may be prolonged in some patients.
Use in lactation. (See Section 4.3 Contraindications.)
The use of Zoladex during breast feeding is not recommended.
4.7 Effects on Ability to Drive and Use Machines
There is no evidence that Zoladex 10.8 mg results in impairment of ability to drive or operate machinery.
4.8 Adverse Effects (Undesirable Effects)
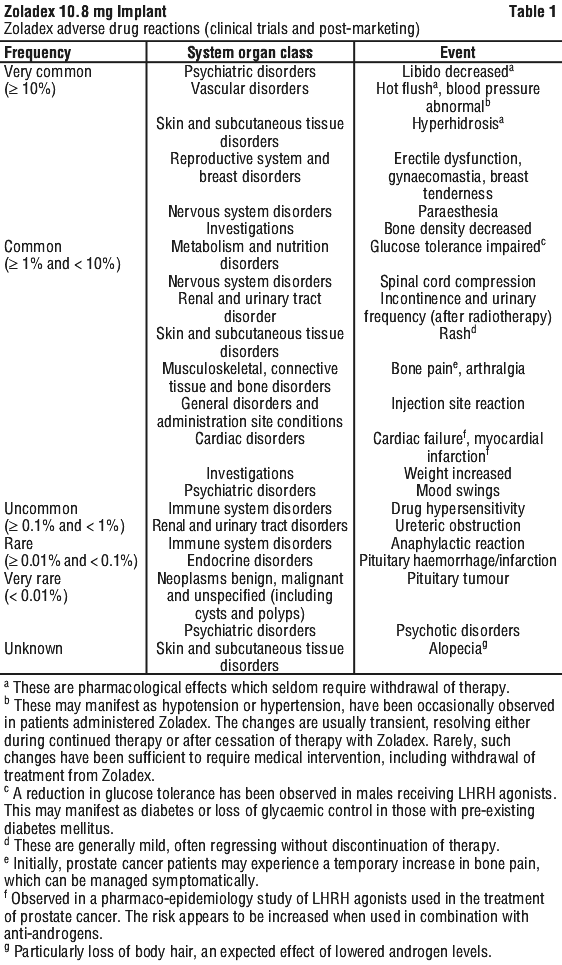
The following frequency categories for adverse drug reactions (ADRs) were calculated based on reports from Zoladex clinical trials and post-marketing sources. See Table 1.
4.9 Overdose
There is limited experience of overdosage in humans. In cases where Zoladex has unintentionally been readministered early or given at a higher dose, no clinically relevant adverse effects have been seen. Animal tests suggest that no effect other than the intended therapeutic effects on sex hormone concentrations and on the reproductive tract will be evident with higher doses of Zoladex. If overdosage occurs, this should be managed symptomatically.
For information on the management of overdose, contact the Poison Information Centre on 131126 (Australia).
5 Pharmacological Properties
5.1 Pharmacodynamic Properties
Mechanism of action. Goserelin acetate is a GnRH agonist (also known as LHRH agonist).
Goserelin acetate is a potent synthetic decapeptide analogue of LHRH. When given acutely, goserelin acetate will release luteinising hormone (LH) from the pituitary gland. However, following chronic administration, goserelin acetate is a potent inhibitor of gonadotrophin production resulting in gonadal suppression and consequently sex organ regression.
In animals and humans, following an initial stimulation of pituitary LH secretion and a transient elevation in serum testosterone in males, or serum oestradiol in females, chronic administration results in inhibition of gonadotrophin secretion. The result is a sustained suppression of pituitary LH occurring within approximately 3 weeks after initiation of therapy. This suppression of gonadal hormones is then maintained as long as therapy is continued.
In men, by around 21 days after the first implant injection, testosterone concentrations have decreased to within the castrate range and remain suppressed with treatment every 3 months. If in exceptional circumstances repeat dosing does not occur at 3 months, data indicate that castrate levels of testosterone are maintained for up to 16 weeks in the majority of patients.
In women, serum oestradiol concentrations are suppressed by around 4 weeks after the first implant injection and remain suppressed until the end of the treatment period at levels comparable with those observed in postmenopausal women. Suppression of oestradiol is associated with a response in hormone-dependent breast cancer in premenopausal women and will result in amenorrhoea in the majority of patients.
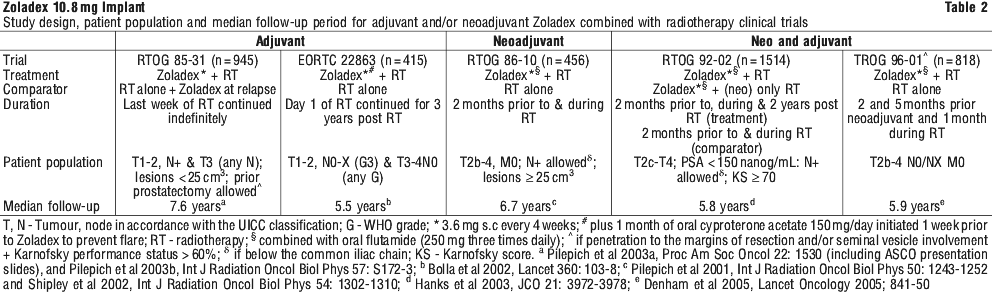
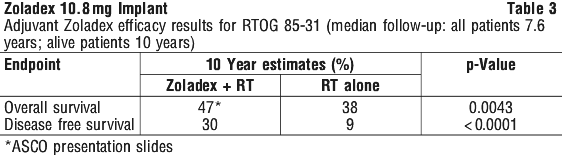
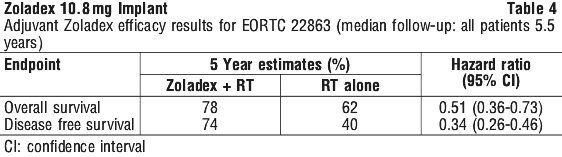
Clinical trials. Prostate cancer - adjuvant and neoadjuvant Zoladex therapy in combination with radiotherapy. Five phase III, open-labelled, randomised, controlled, multi-centred clinical trials have been conducted to evaluate the added value of adjuvant and/or neoadjuvant Zoladex therapy in combination with radiotherapy in patients with histologically proven prostate cancer. The majority of patients had locally advanced disease (T2 N+, T3 or T4, N0/Nx, M0). All studies have been performed by three independent collaborative oncology groups (European Organisation for Research and Treatment of Cancer [EORTC], the Radiation Therapy Oncology Group [RTOG]) and the Trans-Tasman Radiation Oncology Group [TROG]), and have reported results from median follow-up of more than 5 years. Table 2 summarises the study design, patient populations and median follow-up periods for these studies.
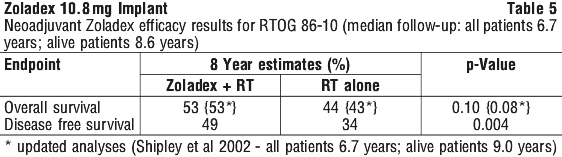
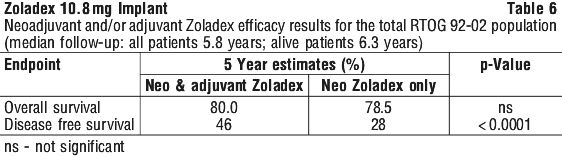
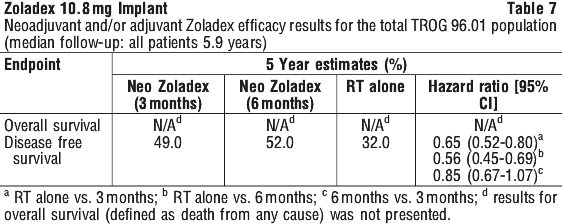
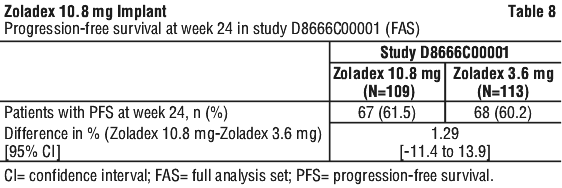
The primary endpoint of the study was progression-free survival (PFS) at week 24. In total, 61.5% (n = 67) of patients in the Zoladex 10.8 mg group and 60.2% (n = 68) of patients in the Zoladex 3.6 mg group were progression free at 24 weeks (treatment difference: 1.3; 95% CI -11.4, 13.9; see Table 8). The lower bound of the 95% CI was above the pre-defined margin of -17.5%, and therefore Zoladex 10.8 mg met the criteria for non-inferiority compared with Zoladex 3.6 mg.
Study D8664C00008. In a Phase III, open-label, randomised, multicentre study in 98 premenopausal women with ER-positive advanced breast cancer, Zoladex 10.8 mg every 12 weeks plus tamoxifen 20 mg daily was compared to Zoladex 3.6 mg every 4 weeks plus tamoxifen. Patients in this trial were Japanese (39.8%) or Caucasian (60.2%). Median age was 43.0 years (range: 26, 59). Recruitment ended early due to changes in treatment practice; 98 of 260 planned patients were randomised, and the study was underpowered to formally demonstrate non-inferiority for PFS at Week 24. PFS at Week 24 was 69.4% with Zoladex 10.8 mg and 73.5% with Zoladex 3.6 mg (treatment difference -4.1%; 95% CI: -21.4, 13.6). Mean serum oestradiol concentrations at Week 24 were 7.24 picomol/L in the 10.8 mg group vs 10.36 picomol/L in the 3.6 mg group. After adjusting for treatment group and baseline oestradiol serum concentrations as covariates, the ratio of the least square means of oestradiol concentrations for the 10.8 mg group compared to the 3.6 mg group at 24 weeks was 0.93 (95% CI 0.60, 1.46).
Premenopausal women with oestrogen receptor-positive early breast cancer. Study D8664C00004. A Phase II, open-label, randomised, parallel group, multicentre study was conducted to compare oestradiol suppression between Zoladex 10.8 mg given once every 12 weeks and Zoladex 3.6 mg given once every 4 weeks in premenopausal patients with ER-positive early breast cancer (Study D8664C00004). All patients also received concomitant oral tamoxifen (20 mg daily). One hundred and seventy patients were randomised into the study; 86 patients to the Zoladex 10.8 mg group and 84 patients to the Zoladex 3.6 mg group. Most patients had invasive breast cancer (95.3%) that was PgR-positive (94.7%), and stage T1 (60.6%). All patients were Japanese. Median age was 44.0 years (range: 26, 53).
The primary objective for this study was to examine whether Zoladex 10.8 mg depot was non-inferior to Zoladex 3.6 mg by assessment of AUC of oestradiol concentration from week 4 to week 24 of treatment.
The geometric mean of oestradiol AUC4-24 week was 67.25 picomol/L per week in the Zoladex 10.8 mg group and 69.56 picomol/L per week in the Zoladex 3.6 mg group. The AUC ratio of the Zoladex 10.8 mg/Zoladex 3.6 mg group, adjusted by baseline oestradiol value, was 0.974 (95% CI: 0.799 to 1.188). The 95% CI upper limit was below the predefined non-inferiority margin of 1.25, indicating that Zoladex 10.8 mg is non-inferior to Zoladex 3.6 mg in terms of oestradiol suppression in premenopausal women with ER-positive breast cancer.
After week 4, the mean oestradiol serum concentrations were maintained below 110 picomol/L in most patients (≥ 98.8%) in both the Zoladex 10.8 mg and Zoladex 3.6 mg groups, i.e. within a post-menopausal range. Most of the patients (98.2%) in both treatment groups had no menstruation after week 8. Mean FSH serum concentrations after week 4 in the range of 1.283 IU/L to 2.117 IU/L in both treatment groups.
5.2 Pharmacokinetic Properties
Goserelin acetate has a serum elimination half-life of approximately 4.2 hours in subjects with normal renal function compared to 13 minutes for natural LHRH.
Although the half-life is increased in patients with impaired renal function, absolute clearance is still relatively rapid. The existence of a non-renal, presumably hepatic, clearance and the absence of an increased incidence of possible adverse reactions in such patients imply that no adjustment in the proposed dosage regimen is necessary in patients with renal impairment.
There is no significant change in pharmacokinetics in patients with hepatic failure.
The implant formulation of the drug is dispersed in a cylindrical rod of a biodegradable and biocompatible polyglactins and is released continuously when injected subcutaneously. The implant is supplied in a purpose-designed applicator with 14-gauge needle.
Administration of Zoladex 10.8 mg, in accordance with the dosage recommendations, ensures that exposure to goserelin is maintained with no clinically significant accumulation. The peak serum concentrations occur during the first 24 hours post administration. In studies of prostate cancer patients, the mean serum concentration at 2 hours post administration is 8.6 ± 2.9 (SD) nanogram/mL with an inter-individual range of up to 11-fold.
Mean systemic clearance values for goserelin were about 100 to 200 mL/min with an inter-individual range of up to 6-fold.
Serum goserelin concentrations become low by end of the dosing interval; delaying or omitting scheduled doses should be avoided as it may lead to increased testosterone or oestradiol levels and loss of efficacy in prostate or breast cancer patients, respectively.
5.3 Preclinical Safety Data
Genotoxicity. Mutagenicity tests for gene mutations and chromosomal damage have provided no evidence for mutagenic effects.
Carcinogenicity. After subcutaneous implant injections once every 4 weeks for 1 year to male and female rats at doses equivalent to 1.8 times the recommended dose for a human (based on AUC), an increased incidence of benign pituitary microadenomas was found.
This finding is similar to that previously noted in this species following surgical castration and appears to be a species specific response to castration. Any relevance to humans has not been established. No increase in pituitary adenomas was seen in mice receiving injections of goserelin every 3 weeks for 2 years at doses up to 2400 microgram/kg/day (approximately 9 to 18 times the recommended dose for a human [based on Cmax]). An increased incidence of histiocytic sarcomas of the bone marrow of the vertebral column and femur were observed in male mice given 2400 microgram/kg/day but not in female mice, or rats of either sex. The relevance of these tumours to humans has not been established.
In mice, long-term repeated dosing with multiples of the human dose produced histological changes in some regions of the digestive system manifested by pancreatic islet cell hyperplasia and a benign proliferation condition in the pyloric region of the stomach, also reported as a spontaneous lesion in this species. The clinical relevance of these findings is unknown.
6 Pharmaceutical Particulars
6.1 List of Excipients
Zoladex 10.8 mg SafeSystem Implant contains the excipient polyglactin.
6.2 Incompatibilities
Incompatibilities were either not assessed or not identified as part of the registration of this medicine.
6.3 Shelf Life
In Australia, information on the shelf life can be found on the public summary of the Australian Register of Therapeutic Goods (ARTG). The expiry date can be found on the packaging.
6.4 Special Precautions for Storage
Store below 25°C.
6.5 Nature and Contents of Container
Zoladex 10.8 mg SafeSytem Implant is supplied as a sterile, biodegradable cylindrical implant containing the equivalent of 10.8 mg of goserelin base together with the inactive ingredient polyglactin and is presented as 1x (one) pre-filled syringe applicator for subcutaneous injection per carton.
6.6 Special Precautions for Disposal
In Australia, any unused medicine or waste material should be disposed of by taking to your local pharmacy.
6.7 Physicochemical Properties
Chemical structure.
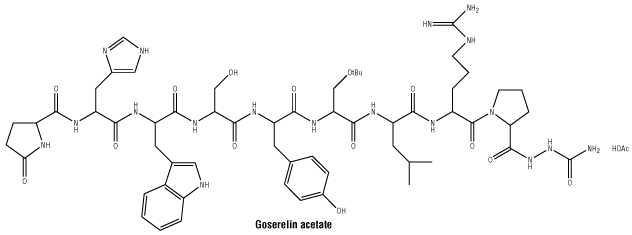
Molecular weight: 1269 (base).
CAS number. 65807-02-5 (goserelin base).
7 Medicine Schedule (Poisons Standard)
Prescription only medicine (Schedule 4).
Date of First Approval
22 May 1996
Date of Revision
28 August 2026
Summary Table of Changes

Reasonable care is taken to provide accurate information at the time of creation. This information is not intended as a substitute for medical advice and should not be exclusively relied on to manage or diagnose a medical condition. The Australian Commission on Safety and Quality in Health Care disclaims all liability (including for negligence) for any loss, damage, injury or any other negative effects resulting from reliance on or use of this information. Read our full disclaimer. This website uses cookies. Read our privacy policy.